Key takeaway
- How AI is used across drug discovery and development, what FDA and EMA say, what the evidence shows and the controls leaders need. Not medical advice.
AI helps drug discovery and development at specific, separable stages: finding and validating targets, designing and screening molecules, predicting properties such as ADMET, planning trials and finding existing drugs for new uses. The evidence differs by stage. Protein structure prediction was recognised in the 2024 Nobel Prize in Chemistry, while the first randomised phase 2a trial of a generative-AI-discovered drug, reported in Nature Medicine, 2025, was a 12-week study whose authors say it warrants larger and longer trials. For a related view of AI in clinical imaging, see AI-assisted medical imaging.
For enterprise leaders the question is less "does AI work" and more "where is it credible, what must be controlled and what will a regulator ask for". Regulators have started to answer: the FDA draft guidance on AI to support regulatory decision-making (January 2025) and the EMA and FDA joint principles (January 2026) both centre on a defined context of use and risk-based evidence. This article is general information, not medical or regulatory advice.
Where does AI fit in the drug discovery and development pipeline?
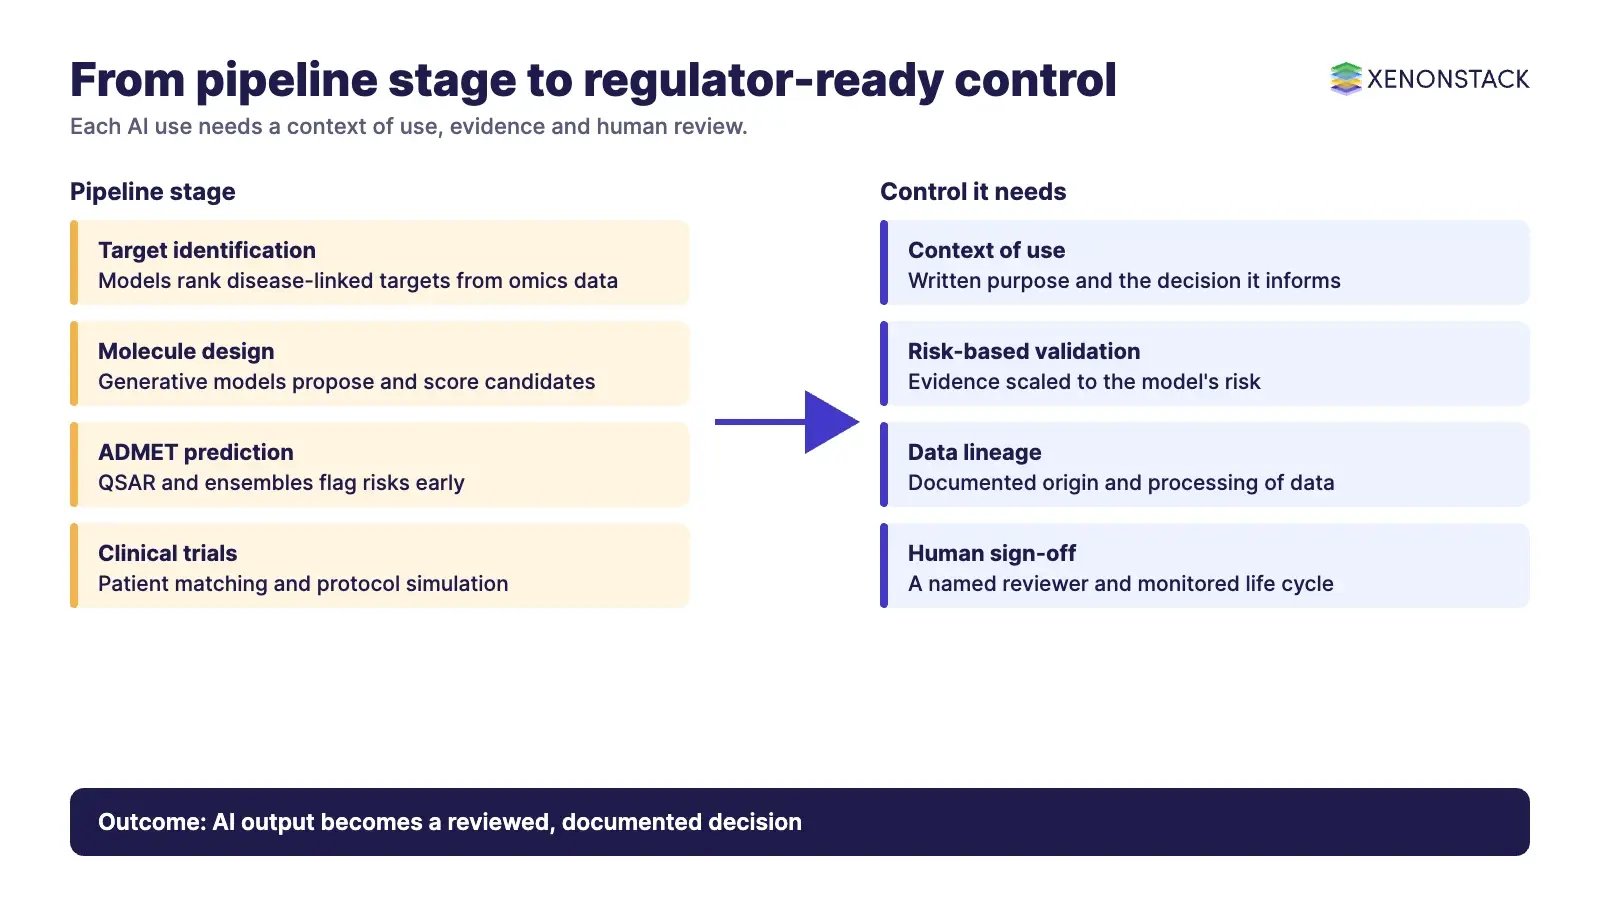
Think of AI as a set of tools placed at different points in a long pipeline, not as one system. The table shows what each stage uses it for and how to read the evidence.
| Stage | What AI is used for | Typical methods | How to read the evidence |
|---|---|---|---|
| Target identification | Ranking disease-linked genes and proteins from omics data | Machine learning, graph neural networks, knowledge graphs | Method level. Validate in the laboratory before any programme decision. |
| Protein structure | Predicting 3D structure to inform target and binding studies | Deep learning structure prediction | Recognised in the 2024 Nobel Prize in Chemistry (Hassabis and Jumper, with Baker for protein design). |
| Molecule design and screening | Generating and scoring candidate molecules | Generative models, docking with learned scoring | One generative-AI-discovered candidate reached a phase 2a trial (see below). Treat other claims as unproven until published. |
| ADMET prediction | Flagging absorption, toxicity and clearance risks early | QSAR, ensemble models | Useful for triage. Predictions still need experimental confirmation. |
| Clinical trials | Patient matching, protocol simulation, monitoring | NLP on records, Bayesian and simulation models | Covered by regulator expectations on context of use and data quality. |
| Repurposing | Finding new uses for existing drugs | Knowledge graphs, similarity search, link prediction | Generates hypotheses, not clinical conclusions. |
How does AI help identify and validate drug targets?
Genomic and proteomic data analysis
Machine learning models can sort large genomic and proteomic datasets for patterns linked to disease, which gives scientists a ranked list of candidate targets to test. Structure prediction adds a second input: knowing a protein's shape helps judge whether a small molecule could bind it. The 2024 Nobel Prize in Chemistry recognised protein structure prediction (Demis Hassabis and John Jumper) and computational protein design (David Baker).
Network biology and systems pharmacology
Multi-omics data (genomics, transcriptomics, proteomics, metabolomics) can be represented as a graph of genes, proteins, drugs and diseases. Graph neural networks and knowledge graphs then look for links a human reviewer would miss. The same pattern is described in our post on Graph RAG and knowledge graphs. The output is a hypothesis. Target validation still depends on experiments, and a graph is only as good as the provenance of the data feeding it.
How is AI used in virtual screening, molecular design and ADMET?
Virtual screening and docking
Virtual screening ranks large compound libraries by predicted interaction with a target. AI adds learned scoring functions to docking simulations, which can change the ranking compared with physics-only scoring. The shortlist goes to laboratory assays, so the practical gain is fewer compounds to test, not fewer experiments to run.
De novo design with generative models
Variational autoencoders, generative adversarial networks and reinforcement learning can propose new molecules and optimise them towards goals such as potency and drug-likeness. Generated structures still need to be synthesised, tested and checked for toxicity. Responsible use is covered in our post on responsible AI in healthcare.
ADMET prediction
ADMET stands for absorption, distribution, metabolism, excretion and toxicity. QSAR models and ensemble methods such as random forests and gradient boosting estimate these properties from chemical structure so that weak candidates can be dropped early. Their reliability depends on training data close to the chemistry being tested, so record the applicability domain of each model.
What does the evidence show so far for AI-discovered drugs?
The most useful public reference point is a Nature Medicine, 2025 report titled "A generative AI-discovered TNIK inhibitor for idiopathic pulmonary fibrosis: a randomized phase 2a trial". According to the published abstract, participants received rentosertib at one of three regimens or placebo for 12 weeks, adverse event rates were similar across groups, and discontinuations were mainly due to liver toxicity or diarrhoea. The authors conclude that the drug appears safe and well tolerated and that larger, longer trials are warranted.
Read this as an early-stage signal, not as proof of efficacy. A phase 2a trial is small and short, and the result says nothing about the other AI-derived candidates in the industry. Ask any vendor or partner for the peer-reviewed or regulator source behind each claim. For AI use in agentic pharma content and discovery workflows, see Agentic AI in pharma.
How does AI optimise clinical trials?
Patient stratification and recruitment
Natural language processing can read electronic health records and real-world data to flag patients who may meet inclusion criteria, and predictive models can estimate who is likely to complete a protocol. Both uses touch personal health data, so privacy review and a clear context of use come before any model goes near a trial.
Adaptive designs and simulation
Bayesian models and reinforcement learning are used to simulate trial designs and to support mid-trial adjustments set out in the protocol in advance. Any adaptation must be pre-specified and agreed with the regulator. AI does not remove that requirement.
What about personalised medicine and drug repurposing?
Machine learning on genomic and clinical data can suggest biomarkers linked to treatment response, using methods such as support vector machines and deep learning. Knowledge graphs, link prediction and similarity measures such as the Tanimoto coefficient can point to existing drugs worth testing for a new disease. Both produce hypotheses for clinical teams to evaluate. Neither replaces clinical judgement or trial evidence.
What are regulators saying about AI in drug development?
Two regulators have published positions, and both frame AI use around the question it answers and the risk of getting it wrong.
| Source | Date | What it says | Status |
|---|---|---|---|
| FDA, considerations for AI to support regulatory decision-making for drugs and biologicals | January 2025 | Recommendations on a risk-based credibility assessment framework for a specific context of use | Draft, non-binding. Check the FDA page for the current status. |
| EMA, reflection paper on AI in the medicines lifecycle | Consultation from July 2023 | Covers AI from drug discovery to post-authorisation. Takes a human-centric approach and advises early regulatory engagement where an AI system may affect benefit-risk | Reflection paper. EMA's January 2026 page refers to its 2024 paper. |
| EMA and FDA, Guiding Principles of Good AI Practice in Drug Development | January 2026 | Ten principles across all phases of a medicine, from early research and clinical trials to manufacturing and safety monitoring | Principles. EMA says additional EU guidance will follow. |
| FDA, plan on new approach methodologies | 10 April 2025 | Encourages computer modelling and AI-based models alongside other methods to reduce animal testing for monoclonal antibodies and other drugs | Announcement and roadmap. |
The ten joint principles, as titled in the Guiding Principles of Good AI Practice in Drug Development, are: human-centric by design; risk-based approach; adherence to standards; clear context of use; multidisciplinary expertise; data governance and documentation; model design and development practices; risk-based performance assessment; life cycle management; and clear, essential information. EMA also publishes its EMA reflection paper on AI in the medicines lifecycle.
What governance, data and cost controls does an AI drug discovery programme need?
The joint principles translate into controls an enterprise can put in place. Each row maps a principle to an operating practice.
| Control | What it means in practice | Principle it supports |
|---|---|---|
| Context of use register | Each model has a written purpose, scope and the decision it informs | Clear context of use |
| Data lineage and documentation | Record where data came from, how it was processed and who approved it | Data governance and documentation |
| Risk-tiered validation | More evidence for models that influence safety or efficacy decisions | Risk-based approach and performance assessment |
| Human review | A named scientist signs off model-informed decisions | Human-centric by design |
| Monitoring and re-evaluation | Track drift when data or chemistry changes and re-test periodically | Life cycle management |
| Cost tracking | Meter compute and experiment spend per model and per programme | Not a regulator requirement, an enterprise practice |
Where agents or automated pipelines touch these steps, the decision trail matters as much as the model. ElixirData Context OS keeps governed context, versioned policy and decision traces in one decision layer above AI agents, and AgentGRC keeps autonomous agent actions inside policy, with the audit trail risk teams need. Related reading: Agentic AI in data governance and compliance and Agentic AI risk management.
How should a pharma or biotech team sequence adoption?
Pick one decision with a clear owner, such as ADMET triage or trial site feasibility, and write its context of use.
Fix the data first: lineage, access rights, privacy review and a documented training set.
Run the model beside the current method and compare results on past, known outcomes before it influences any live decision.
Set the evidence bar by risk, and confirm early with the regulator where the model could affect benefit-risk.
Add monitoring and re-evaluation, then widen to the next stage.
When is AI the wrong tool, and what are the trade-offs?
| Situation | Why AI may not fit | Safer approach |
|---|---|---|
| Little or poor-quality data for the target or chemistry | Models extrapolate badly outside their training data | Rely on experiments and expert review, collect data first |
| Decision with direct patient safety impact | Black-box output is hard to justify to a regulator | Use interpretable methods and keep human sign-off |
| No owner for the model after launch | Performance drifts and nobody notices | Assign life cycle ownership before deployment |
| Claim cannot be traced to a source | Vendor or internal claims without evidence create risk | Ask for the peer-reviewed or regulator source |
What will change in AI-enabled drug development over the next 3 to 5 years?
Public sources point to regulation becoming more specific rather than to any single technology jump. EMA states that the January 2026 principles will be supplemented by additional EU guidance, and the FDA guidance from January 2025 is labelled as a draft. Teams that already keep a context-of-use register, data lineage and monitoring records will adapt more easily as these documents are finalised. Trial results for AI-discovered candidates will also accumulate, which is the evidence to watch.
To map one drug-development decision your agents should make, and the context and policy it depends on, book a Context Workshop. See what happens in the workshop.
What should you plan for in 2027?
The points below come from the controls and adoption steps already set out above, and they apply to any programme that uses AI.
- Write the context of use first. Record each model's purpose, scope and the decision it informs, with a named scientist who signs off.
- Set the evidence bar by risk. Ask more of models that influence safety or efficacy decisions, and engage the regulator early where benefit and risk could be affected.
- Keep data lineage and monitoring in place. Track drift, test again periodically and keep documentation that regulators can review.
Teams that already work this way will adapt more easily as guidance develops.
Frequently asked questions
Is AI-discovered drug development proven?
Not broadly. A randomised phase 2a trial of a generative-AI-discovered drug was published in Nature Medicine in 2025. It was a 12-week study, and its authors say larger and longer trials are warranted.
What does the FDA say about AI in drug development?
In January 2025 the FDA published draft, non-binding guidance recommending a risk-based credibility assessment framework for AI used to support regulatory decisions on drug safety, effectiveness or quality. Check the FDA page for current status.
What are the EMA and FDA joint principles?
In January 2026 EMA and the FDA jointly identified ten principles for good AI practice across the medicines lifecycle, including a risk-based approach, a clear context of use, data governance and documentation, and life cycle management.
Does AI replace laboratory experiments?
No. AI narrows candidates and generates hypotheses. Targets, molecules and predictions still need experimental and clinical confirmation.
What should leaders ask before adopting AI in drug discovery?
Ask what decision the model informs, what data it was trained on, what evidence supports it, who reviews its output and how it will be monitored over time.
Follow XenonStack on LinkedIn: XenonStack on LinkedIn for new guides on agentic AI, data and platform engineering.
Ready to put AI agents to work? Explore ElixirClaw, the agentic OS platform to build, orchestrate and govern AI agents.
Explore the XenonStack platform family: ElixirData · ElixirClaw · ElixirHub · NexaStack · MetaSecure · Neural AI · AgentGRC · AgentSRE · AgentAnalyst · AgentInstruct · AgentRAI · AgentScrum · AgentSearch · AgentForce · AI Aviator · SAIF Aviator · CohortIQ · XenonStack AI · XenonStack UAE