

Key takeaway
- How agentic AI in pharma supports drug discovery and regulatory content, what FDA and EMA have said, and how to govern and adopt agents safely.
Agentic AI in pharma means software agents that plan and carry out multi-step work, such as screening a target, assembling a regulatory document or checking a safety report, while people keep the decisions that carry scientific or legal weight. It fits best where the work is long, document-heavy and rule-bound: early drug discovery, clinical and regulatory content, and pharmacovigilance. It fits poorly where a single error cannot be caught before it reaches a patient or a regulator.
This guide is written for pharma CIOs, Chief AI Officers, heads of R&D and regulatory IT, and enterprise architects. It covers where agents help in drug discovery and content management, what regulators have said so far, how to govern agents, and a sequence for adopting them. For the wider clinical picture, see our guide to agentic AI in healthcare systems, and for the supply side, AI in the biopharmaceutical supply chain.
What is agentic AI in pharma and how does it differ from earlier AI?
Earlier pharma AI mostly answered one question at a time: predict a property, classify a document, rank a list. Agentic AI adds a loop. An agent is given a goal, breaks it into steps, calls tools and data sources, checks the result and decides what to do next, within limits set by people. In a regulated setting the limits matter more than the autonomy: which systems the agent may read, what it may write, and which steps need a named human to approve.
| Approach | What it does | Where it fits in pharma | Main limit |
|---|---|---|---|
| Predictive model | Scores or classifies one input | Property prediction, document classification | Needs a person to chain the steps |
| Generative assistant | Drafts text or structures on request | First drafts of summaries and sections | No plan, no tool use, no memory of the task |
| Agent with tools | Plans, calls systems, checks results, escalates | Literature review, screening workflows, document assembly, case triage | Needs access controls, logging and validation |
Where does agentic AI fit in drug discovery?
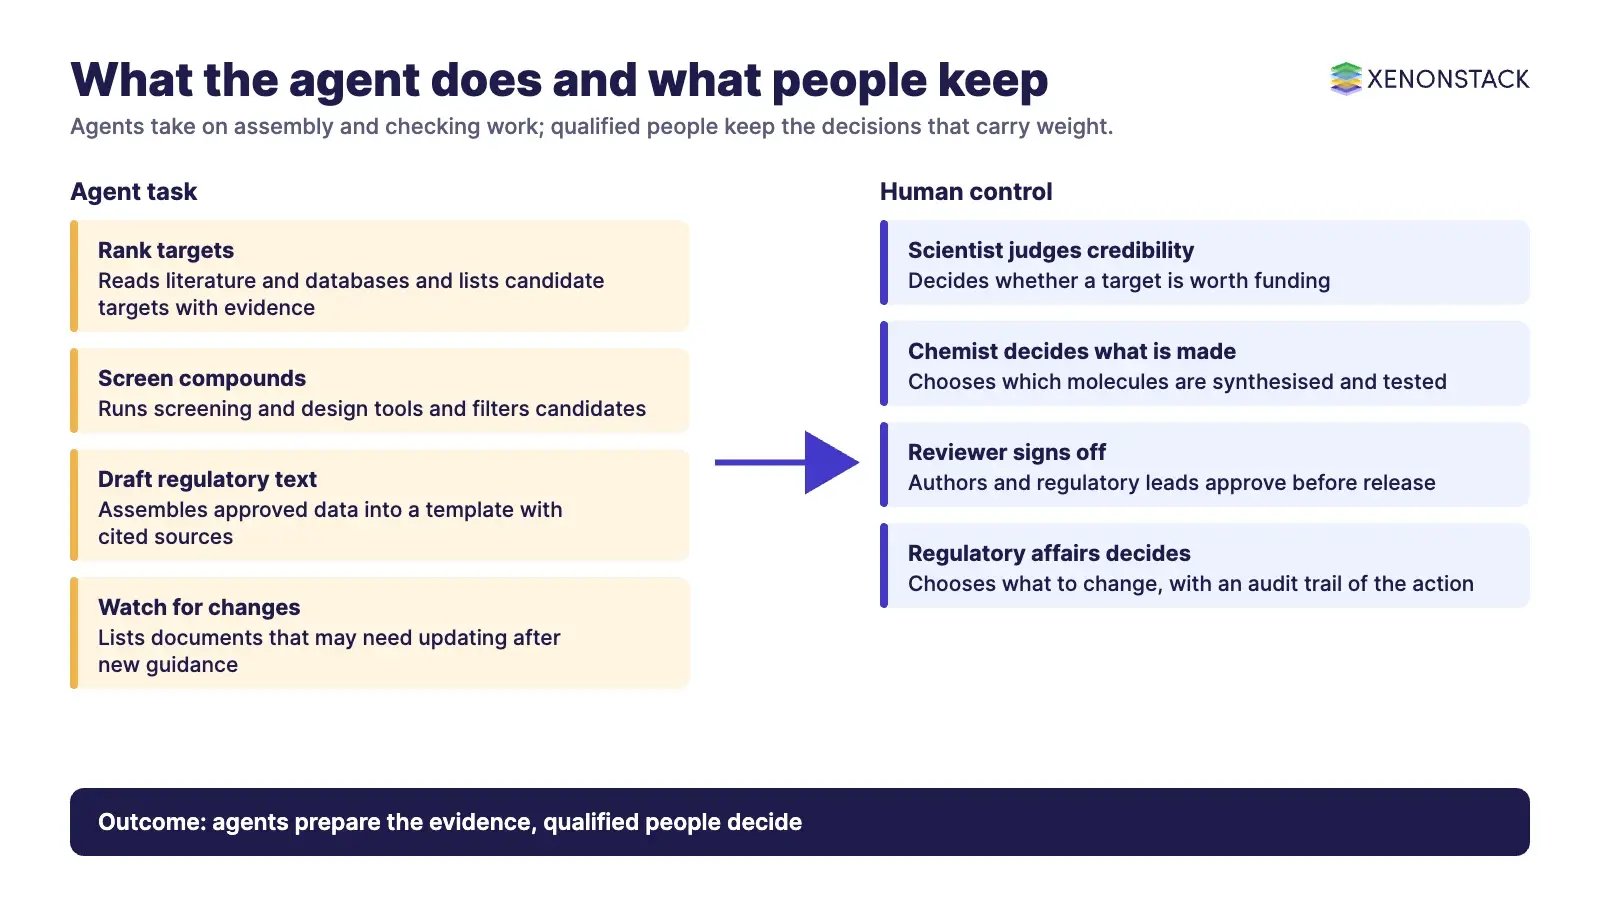
Drug discovery is long, costly and high-risk, and much of it is repeated analysis across many data sources. That is where agents can take on work. The table maps each stage to the agent task, the decision a scientist keeps, and the strength of public evidence.
| Stage | What an agent can do | What a scientist still decides | Evidence status |
|---|---|---|---|
| Target identification | Reads literature, omics and public databases; ranks candidate targets with the evidence behind each | Whether a target is biologically credible and worth funding | Published case: a generative AI approach identified TNIK as a target in idiopathic pulmonary fibrosis (see below) |
| Compound screening and design | Runs virtual screening and generative design tools, filters candidates, suggests molecules to synthesise | Which molecules are synthesised and tested | Company-reported speed gains; independent comparison data is limited |
| Modelling and simulation | Sets parameters, reruns simulations, flags results that disagree with assay data | Whether a model is valid for the question being asked | Depends on the model and the data; validate per use |
| Workflow orchestration | Raises requests to labs, tracks tests, assembles the evidence pack for a candidate | Approvals, budget and priorities | Operational, low scientific risk when logged |
| Clinical trial support | Proposes cohort criteria, flags enrolment risks, drafts protocol sections for review | Protocol design, eligibility and any change to a running trial | Regulated; follow the sponsor and regulator rules for the use |
What has one AI-designed drug shown so far?
The best-documented public case is Insilico Medicine's rentosertib (ISM001-055), a small-molecule TNIK inhibitor for idiopathic pulmonary fibrosis. A Phase IIa trial (GENESIS-IPF) in 71 patients at 22 sites in China, published in Nature Medicine on 3 June 2025, reported a mean forced vital capacity gain of 98.4 mL in the 60 mg once-daily group against a mean decline of 20.3 mL on placebo over 12 weeks. The company also states that its 22 candidates nominated between 2021 and 2024 took 12 to 18 months on average from project start to preclinical candidate nomination, against a typical 2.5 to 4 years. Those timing figures are the company's own, as reported in its press release. The trial was small and short, so it is early evidence, not proof of approval. Source: EurekAlert news release.
How does agentic AI help with regulatory and medical content?
Pharma companies maintain regulatory submissions, clinical study reports, standard operating procedures (SOPs), labelling, medical information responses and promotional material. Each has to be accurate, consistent and traceable to a source. Agents can do the assembly and checking work, with reviewers approving what is released. Governed retrieval matters here: AgentSearch is ElixirData's context-aware enterprise search across unstructured knowledge bases, which respects access rules and runs under Context OS governance.
| Content task | What the agent does | Human control | Risk if unchecked |
|---|---|---|---|
| First drafts of regulatory sections | Pulls approved data and prior text into a template and cites each source | Authors and regulatory leads review and sign off | Unsupported statements enter a submission |
| Consistency checks | Compares terminology, claims and numbers across documents | Reviewer resolves each flagged difference | False positives waste time; missed conflicts persist |
| Change monitoring | Watches regulator and publication feeds and lists documents that may need updates | Regulatory affairs decides what to change | Acting on a misread update |
| Knowledge retrieval | Finds related studies, trial data and past agency feedback and summarises with citations | Scientist checks the cited passages | Answers without a source |
| Localisation | Prepares translations that keep approved terms | Local reviewers approve before use | Meaning drift in safety-critical text |
For compliance evidence across these workflows, AgentGRC keeps autonomous actions inside policy and records evidence that audit and risk teams can review.
What have regulators said about AI in the medicines lifecycle?
Guidance is still taking shape, and parts of it are drafts. Check each source for the latest status before relying on it.
| Source | What it says | Status (as read 12 Nov 2026) | Why it matters for agents |
|---|---|---|---|
| FDA, Considerations for the Use of AI to Support Regulatory Decision-Making for Drug and Biological Products | Sets out a risk-based credibility assessment framework for AI models used for a particular context of use | Draft guidance, January 2025; non-binding recommendations | Define the context of use for each agent and evidence its credibility for that use |
| EMA, Reflection paper on the use of AI in the medicinal product lifecycle | Covers AI and machine learning at any step from drug discovery to the post-authorisation setting, for human and veterinary medicines | Adopted version first published 30 September 2024 | A reflection paper signals expectations; it is not a licence to skip validation |
| 21 CFR Part 11 | Criteria for trustworthy electronic records and signatures; section 11.10(e) calls for secure, computer-generated, time-stamped audit trails | In force | Agent actions that create or change regulated records need audit trails and validated systems |
What are the governance, security and cost risks?
How do we keep agent actions auditable?
Log every agent step: the goal, the data read, the tool called, the output and the human who approved it. Version the policies and prompts the agent runs under, so a past decision can be reconstructed. ElixirData Context OS keeps governed context, versioned policy and decision traces in one decision layer above AI agents, which suits this need.
What data problems break agents?
Agents are only as reliable as the data they can reach. Siloed systems, inconsistent identifiers and uncontrolled document versions produce confident but wrong outputs. Fix the source of truth for each content type before giving an agent write access.
How should patient and research data be protected?
Give each agent the least access it needs, separate research data from patient data, and apply the data protection law that governs the records involved, such as GDPR where personal data of people in the EU is processed. Treat prompts and outputs as records that can contain sensitive data.
What drives cost?
The visible cost is model and tooling spend. The larger costs are usually validation effort, integration with document and laboratory systems, and reviewer time. Budget for them from the start, and measure reviewer time saved, not drafts produced.
When should pharma teams not use agents?
| Situation | Why to hold back | Safer option |
|---|---|---|
| Final decisions on safety, dosing or eligibility | An error can reach patients and cannot be caught later | Use an agent to prepare evidence, with a qualified person deciding |
| Regulated records with no audit trail in the toolchain | Part 11 style controls cannot be shown | Fix logging and validation first |
| Data that is incomplete or ungoverned | Outputs cannot be trusted or traced | Clean and catalogue the data, then pilot |
| Tasks that run well as a fixed script | An agent adds variability without benefit | Keep deterministic automation |
How should a pharma team sequence adoption?
Choose one read-only workflow. Literature review or document consistency checking is a sensible start, because the agent only reads and reports.
Define the context of use. Write down the question the agent answers, the data it may read and the decision it must never make.
Add logging and policy. Record every step and put approval gates on any write action.
Validate against expert work. Compare agent outputs with those of qualified staff on a fixed test set before wider use.
Extend to drafting and orchestration. Allow draft creation and task routing once review time and error rates are measured.
Review regulatory status each quarter. FDA and EMA material is changing, so recheck the draft and adopted documents.
Teams working in this area also raise safety signal detection and clinical trial intelligence as use cases. Both depend on the same controls: governed data access, evidence for each flag and a qualified reviewer. Our overview of autonomous operations in healthcare covers the operating model.
What is likely to change next?
Two things are worth watching. First, whether FDA finalises its draft credibility framework, since it is the most detailed statement so far on evidencing an AI model for a specific context of use. Second, how EMA and national agencies apply their AI principles in day-to-day reviews. Neither is settled in the documents read for this guide, so plan for change and keep agent designs modular.
To map one pharma decision your agents should make, and the context and policy it depends on, book a Context Workshop. See what happens in the workshop.
FAQ
What is agentic AI in the pharmaceutical industry?
Agentic AI in pharma uses software agents that plan and carry out multi-step tasks, such as literature review, document assembly or case triage, using approved tools and data, with people approving decisions that carry scientific or legal weight.
Has an AI-designed drug reached clinical trials?
Yes. Insilico Medicine's rentosertib, a TNIK inhibitor for idiopathic pulmonary fibrosis, reported Phase IIa results in Nature Medicine on 3 June 2025 from a 71-patient trial. It is early evidence, and the trial was small and lasted 12 weeks.
Does FDA have guidance on AI in drug development?
FDA published draft guidance in January 2025 on using AI to support regulatory decision-making for drugs and biological products. It proposes a risk-based credibility assessment for a defined context of use and is non-binding. Check the FDA page for later changes.
What has EMA said about AI?
EMA's reflection paper on AI in the medicinal product lifecycle covers AI and machine learning from drug discovery to the post-authorisation setting. The adopted version was first published on 30 September 2024.
What controls do agents need in regulated pharma work?
At minimum, least-privilege access, logged and time-stamped actions, versioned policies, human approval for write actions and validation against expert work. 21 CFR Part 11 section 11.10(e) calls for secure, computer-generated, time-stamped audit trails for regulated electronic records.
Follow XenonStack on LinkedIn: XenonStack on LinkedIn for new guides on agentic AI, data and platform engineering.
Ready to put AI agents to work? Explore ElixirClaw, the agentic OS platform to build, orchestrate and govern AI agents.
Explore the XenonStack platform family: ElixirData · ElixirClaw · ElixirHub · NexaStack · MetaSecure · Neural AI · AgentGRC · AgentSRE · AgentAnalyst · AgentInstruct · AgentRAI · AgentScrum · AgentSearch · AgentForce · AI Aviator · SAIF Aviator · CohortIQ · XenonStack AI · XenonStack UAE







