

Key takeaway
- Edge AI in healthcare runs clinical models on devices near the patient for speed and privacy. Architecture, HIPAA, FDA and EU rules, and what comes next.
Edge AI in healthcare means running trained AI models on or near the device that captures patient data, such as a wearable, bedside monitor, portable ultrasound or ambulance gateway, instead of sending every signal to a distant cloud first. The result is faster alerts, care that keeps working when the network does not, and less raw patient data leaving the point of care.
For leaders, the decision is not "edge or cloud". It is which clinical decisions must happen in milliseconds and on-site, which can wait for the cloud, and how both stay inside HIPAA, FDA, EU MDR and EU AI Act obligations. This guide covers that split, the reference architecture, the regulation, an adoption path and the honest limits.
What is edge AI in healthcare, and why does it matter now?
Edge AI combines AI inference with edge computing. The model runs where data is created: a sensor, a medical device, a gateway in a ward, or a small server in a hospital. Only results, alerts or reduced datasets travel onward. Training and heavy analytics usually still happen in the cloud or a data centre.
Three pressures make this a board-level topic now:
- Speed at the point of care. Arrhythmia alerts, sepsis early warnings, imaging triage and ambulance assessment lose value with every second of network round trip.
- Privacy and data minimisation. Processing locally means fewer copies of protected health information (PHI) in transit and at rest elsewhere, which supports HIPAA's minimum necessary standard and GDPR's data minimisation principle.
- Resilience and reach. Rural clinics, home care and mobile units cannot assume reliable connectivity. Edge inference keeps core functions running offline.
The regulatory frame has also matured. The US Food and Drug Administration (FDA) now has specific guidance for AI-enabled device software, and the EU has confirmed that AI in medical devices is treated as high-risk AI. Organisations can now design for compliance rather than guess at it.
How does an edge AI architecture for healthcare work?
Most production designs use three tiers. Each tier has a clear job, and the integration points between them are where most projects succeed or fail.
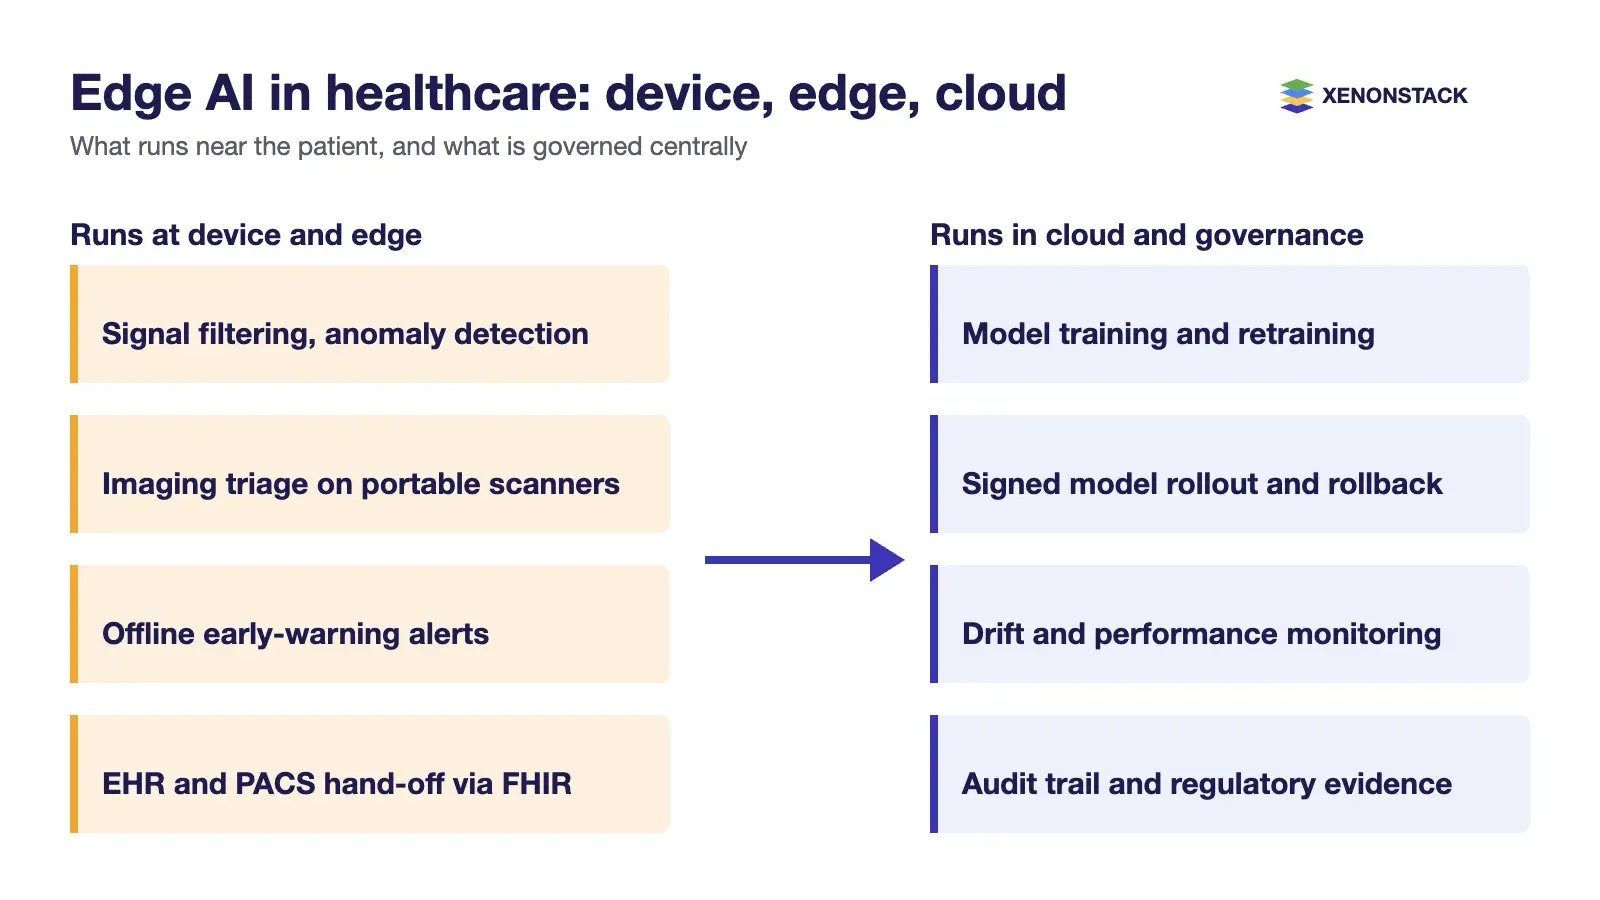
| Tier | Typical hardware | What runs there | Data that leaves it |
|---|---|---|---|
| Device | Wearables, patches, bedside monitors, portable imaging | Signal filtering, small quantised models, threshold and anomaly detection | Alerts, features, short event windows |
| Edge (site) | Ward or department gateway, on-premises GPU server, ambulance compute unit | Larger models (imaging triage, multi-signal early warning), local buffering, EHR and PACS integration | De-identified or minimised data, model metrics, audit logs |
| Cloud or data centre | Hospital private cloud or public cloud | Training and retraining, fleet model management, population analytics, monitoring | Signed model versions pushed back to edge and devices |
Where are the integration points?
- Clinical systems: results must land in the electronic health record (EHR), imaging archive (PACS) or nurse-call system, usually through HL7 v2 or FHIR interfaces, or the alert is never seen.
- Model delivery: signed, versioned model packages, staged rollout and rollback across thousands of devices.
- Identity and security: device identity, encryption in transit and at rest, and patching that does not interrupt clinical use.
- Telemetry: model performance and drift signals sent back without shipping raw PHI.
Where does it break?
The common failure points are model drift that nobody detects because edge devices report too little, version sprawl across a fleet, alerts that never reach a clinician's workflow, and constrained hardware that forces aggressive model compression with a loss of accuracy that was never re-validated. For a wider look at distributed designs, see our guide to edge AI with agentic AI for distributed intelligence.
Where does edge AI deliver value in clinical care?
| Use case | Edge device | Why edge rather than cloud |
|---|---|---|
| Remote patient monitoring | Wearables, patches, home hubs | Continuous signals are large; only events need to travel. Works on weak home broadband. |
| Emergency and pre-hospital care | Ambulance compute unit, portable monitors | Connectivity drops in transit; assessment cannot wait. |
| Point-of-care imaging | Portable ultrasound, mobile X-ray | Immediate triage on-site; large image files stay local. |
| Inpatient early warning | Bedside monitors with ward gateway | Combines several signals in near real time; keeps working during network outages. |
| Telemedicine | Connected diagnostic kits | Pre-processing on the kit improves signal quality and reduces upload size. |
The common thread is time-sensitive decisions on high-volume signals. Where a decision can safely wait minutes or hours, a cloud design is usually simpler. Related patterns appear in applications of edge computing across other industries.
Should you choose device, edge or cloud processing?
| Choose | When | Trade-off to accept |
|---|---|---|
| On-device inference | Response must be sub-second, the device may be offline, or raw data should never leave the patient | Small models, hard fleet updates, limited logging |
| Site edge (gateway or on-premises server) | You need larger models, several data sources, and integration with EHR or PACS inside the hospital | Local infrastructure to run, patch and secure |
| Cloud | Decisions can wait, you need population-level data, or you are training and monitoring models | Latency, connectivity dependence, more PHI in transit |
| Hybrid (most common) | Inference at the device or edge, training and governance in the cloud | More moving parts; needs one view of models, versions and decisions |
Platforms in this space range from device vendor toolkits to general edge orchestration and inference platforms. For example, NexaStack describes itself as an Agentic Operating Platform for Physical AI that runs on-premises, in the cloud and in hybrid set-ups. Evaluate any option on fleet model management, offline behaviour and audit evidence, not on demo accuracy alone.
Which regulations apply to edge AI in healthcare?
Moving inference to the edge does not reduce regulatory scope. It changes where controls must operate. The table summarises the main frameworks; your legal and regulatory teams should confirm how each applies to your product and region.
| Framework | What it means for edge AI |
|---|---|
| HIPAA Security Rule and Privacy Rule (US) | PHI on devices and gateways needs administrative, physical and technical safeguards. The minimum necessary standard supports sending only what each use requires. HHS proposed a major Security Rule update in January 2025; final action is not yet issued. |
| FDA PCCP final guidance (December 2024) | A predetermined change control plan describes planned model changes, the protocol to make them and the impact assessment, so pre-agreed updates can ship without a new submission each time. |
| FDA draft guidance on AI-enabled device software functions (January 2025) | Sets out what marketing submissions should contain and frames risk management across the total product lifecycle. Draft, so non-binding, but a clear signal of expectations. |
| EU MDR (Regulation (EU) 2017/745) | Software that informs diagnostic or therapeutic decisions is a medical device; Annex VIII Rule 11 typically places it in Class IIa or higher, requiring a notified body. |
| EU AI Act (Regulation (EU) 2024/1689), as amended by the Digital Omnibus on AI (Regulation (EU) 2026/1744) | AI that is a safety component of, or is itself, a medical device needing third-party conformity assessment is high-risk AI. After the 2026 amendment, these obligations are scheduled to apply from 2 August 2028, alongside MDR or IVDR. |
| GDPR | Health data is special category data (Article 9). Article 5(1)(c) requires data to be limited to what is necessary, which favours edge processing and minimised uploads. |
How does data minimisation work in practice?
- Process raw waveforms and images locally; send events, features or scores.
- Set retention windows on devices and gateways, and delete buffered data once delivered.
- Use de-identified or pseudonymised data for retraining; consider federated learning where data cannot move.
- Log every model version, input summary and output so a decision can be traced without keeping full raw data.
That traceability is a governance problem, not only an engineering one. ElixirData provides governed context, versioned policy and decision traces in one decision layer above the agents, and AgentGRC supports governance, risk and compliance work around those decisions. For the agentic side of clinical AI, see agentic AI in healthcare: applications, risks and rules.
How should a healthcare organisation adopt edge AI?
- Pick one time-critical decision. For example, an arrhythmia alert from a wearable or triage of a portable chest X-ray. Define who acts on the output and how fast.
- Confirm the regulatory path early. Is it a medical device? Which class? Will you need a PCCP for model updates?
- Design the data flow for minimisation. Decide what stays on the device, what reaches the site edge and what reaches the cloud.
- Build fleet operations before scale. Signed model packages, staged rollout, rollback, monitoring and patching.
- Integrate into clinical workflow. Results in the EHR or nurse-call system, with clear escalation.
- Run a controlled pilot, then expand by site.
Which metrics show it is working?
| Area | Metric |
|---|---|
| Clinical | Time from signal to clinician action; sensitivity and false alert rate against the validated baseline |
| Operational | Uptime during network loss; share of fleet on the approved model version; time to roll back |
| Privacy and compliance | Volume of PHI leaving the site; audit trail completeness; time to answer a regulator's traceability request |
| Cost | Cloud egress and compute avoided versus edge hardware and operations cost |
When is edge AI not the answer?
- When decisions can wait and connectivity is reliable. Cloud is simpler to run and update.
- When the model needs data from many systems at once, such as full EHR history. That belongs in a central tier.
- When you cannot yet operate a device fleet: patching, monitoring and rollback. Edge AI without fleet operations creates unmanaged clinical risk.
- When compression to fit the hardware lowers accuracy below the validated level.
What will change in edge AI in healthcare over the next 3 to 5 years?
- More processing outside the data centre. Gartner has predicted that by 2028 more than two-thirds of enterprise-managed data will be created and processed outside the data centre or cloud, and that more than two-thirds of enterprises will deploy edge AI by 2029, up from 10% in 2025 (as reported by Network World, September 2026). IDC's 2026 FutureScape expects half of enterprise AI inference workloads to run on endpoints or edge nodes by 2030.
- Continuous model updates under pre-agreed plans. With FDA's PCCP guidance final, expect more AI-enabled devices to ship with planned update paths, which makes fleet model management and evidence of each change a core capability.
- Dual EU compliance. From 2 August 2028, AI in medical devices must meet EU AI Act high-risk requirements as well as MDR or IVDR. Expect combined technical documentation and post-market monitoring to become standard.
- Stricter security baselines in the US. The proposed HIPAA Security Rule update, with final action now reported as targeted for July 2027, would tighten expectations on encryption, asset inventories and risk analysis, all of which reach edge devices.
- Governed data reuse in Europe. The European Health Data Space Regulation (EU) 2025/327 phases in from March 2027, with secondary use of health data for research and innovation from March 2029. That creates a lawful route to train models on wider data while inference stays local.
For how agents will run at the edge alongside these models, see agentic AI in edge computing: architecture and use cases.
To map one decision your agents should make, and the context and policy it depends on, book a Context Workshop. See what happens in the workshop.
Frequently asked questions
What is edge AI in healthcare?
It is running trained AI models on or near the device that captures patient data, such as a wearable, monitor or portable scanner, so alerts and results are produced locally instead of waiting for a cloud round trip.
Is edge AI more private than cloud AI?
It can be. Processing raw data locally and sending only events or scores reduces the protected health information in transit and stored elsewhere, which supports HIPAA's minimum necessary standard and GDPR data minimisation. Devices and gateways still need full security controls.
Does FDA regulate edge AI medical devices?
Yes, where the software meets the device definition. FDA issued final guidance on predetermined change control plans for AI-enabled device software in December 2024 and draft lifecycle and submission guidance in January 2025.
How does the EU AI Act affect AI in medical devices?
AI in medical devices that need third-party conformity assessment is high-risk AI. Following the Digital Omnibus on AI, these obligations are scheduled to apply from 2 August 2028, in parallel with the EU MDR or IVDR.
When should healthcare AI run in the cloud instead of at the edge?
When the decision can wait, connectivity is reliable, or the model needs data from many systems at once. Training, retraining and fleet monitoring also usually stay in the cloud.
What is the biggest operational risk with edge AI?
Running a device fleet without proper model management: undetected drift, mixed model versions and no fast rollback. Plan fleet operations before scaling.
Follow XenonStack on LinkedIn: XenonStack on LinkedIn for new guides on agentic AI, data and platform engineering.
Ready to put AI agents to work? Explore ElixirClaw, the agentic OS platform to build, orchestrate and govern AI agents.
Explore the XenonStack platform family: ElixirData · ElixirClaw · ElixirHub · NexaStack · MetaSecure · Neural AI · AgentGRC · AgentSRE · AgentAnalyst · AgentInstruct · AgentRAI · AgentScrum · AgentSearch · AgentForce · AI Aviator · SAIF Aviator · CohortIQ · XenonStack AI · XenonStack UAE






