Key takeaway
- AI ethics and governance in healthcare: principles, risk controls, EU AI Act, FDA and HIPAA starting points, accountability and agent governance.
AI ethics and governance in healthcare is the set of principles, roles and controls that keep clinical and operational AI safe, fair, private, explainable and accountable. The principles are well established; the harder work for a hospital, payer or health-tech company is turning them into owners, tests and records that an auditor or clinician can inspect.
This guide is a governance framework for enterprise leaders. It sits alongside our posts on responsible AI in healthcare, explainability in healthcare AI, AI-assisted medical imaging and agentic AI in healthcare, and focuses on who decides, who is accountable and what evidence is kept. It is general information, not legal or medical advice.
Why does healthcare AI need its own governance?
A wrong output in healthcare can affect a patient, not only a process. Models learn from the data they are given, so a system trained on one population can perform differently on another, and a system built for one clinical question can drift into uses it was never validated for. Governance exists to catch those failures before they reach care, and to show afterwards what was decided and why.
The World Health Organization published "Ethics and governance of artificial intelligence for health" on 28 June 2021, with six consensus principles intended to make sure AI benefits the public in all countries (WHO publication page). Read the report itself for the exact wording of the principles; they are not reproduced here.
What principles should guide ethical AI in healthcare?
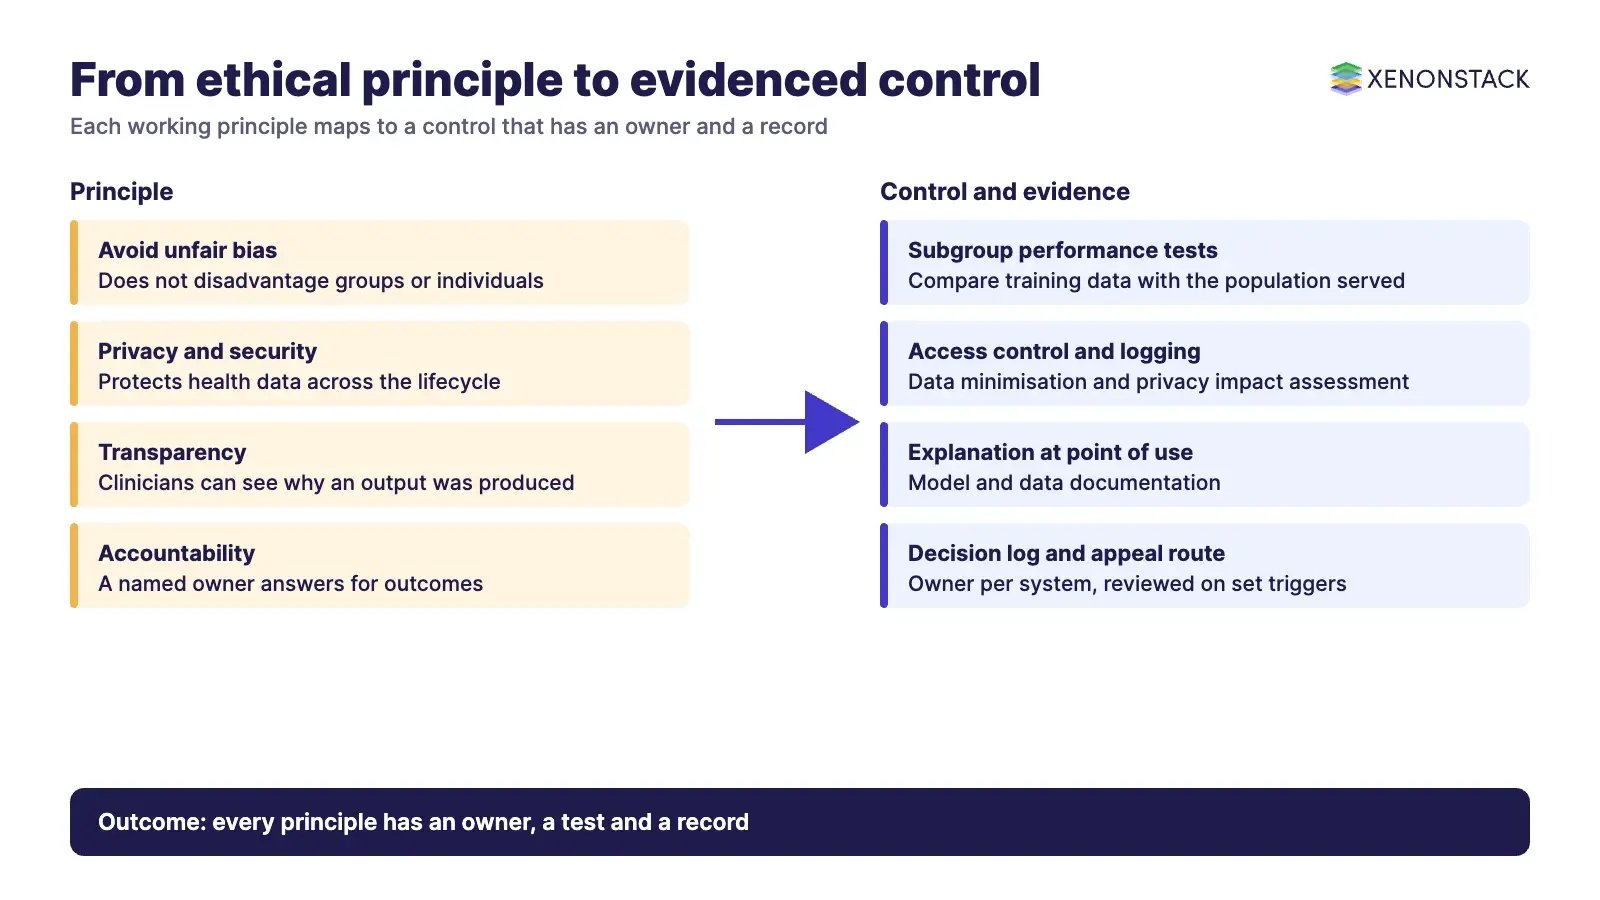
We use nine working principles to structure reviews. They are our own checklist for design and operation, and they overlap with the WHO principles without replacing them. Each is only useful when it maps to a control someone owns.
| Principle | What it asks of the system | Control to put in place |
|---|---|---|
| Social wellbeing | Serves patients, clinicians and society, including where staff are scarce | Documented clinical purpose and benefit case before build |
| Avoid unfair bias | Does not disadvantage groups or individuals | Representativeness check on data; subgroup performance tests; retraining trigger |
| Privacy and security | Protects health data throughout the lifecycle | Data minimisation, access control, logging, privacy impact assessment |
| Reliable and safe | Works only for the validated purpose | Intended-use statement, pre-deployment validation, live monitoring |
| Transparency and explainability | Clinicians can see why an output was produced | Explanation shown at the point of use; model and data documentation |
| Governable | Unintended behaviour is detected and stopped | Override and shut-off route, incident process, drift alerts |
| Value alignment | Respects accepted human and clinical values | Content and behaviour tests, especially for patient-facing chat |
| Accountability | A named owner answers for outcomes | Owner per system, feedback and appeal route, decision log |
| Human-centred | Preserves autonomy, dignity and rights | Human review of consequential decisions; consent and disclosure rules |
How does bias get into a healthcare AI system?
Bias usually enters through the data. If the training set under-represents a group, or reflects past patterns of unequal access to care, the model can reproduce that gap. A system validated in one country, hospital or device fleet can also behave differently when moved to another, because patient mix, disease presentation and equipment all change.
The control is practical: compare the data you trained on with the population you will serve, report performance for each relevant subgroup, and revalidate whenever the setting changes. A model that was built to screen a population should also be re-evaluated, not simply reused, if the team later extends it to diagnosis, because the people it sees and the question it answers are different.
What do regulators and standards bodies say today?
Rules differ by market and change often. The table lists the official starting points and what each page says, read on 13 November 2026. Confirm the current position on each page before relying on it.
| Source | What its page says | Why it matters |
|---|---|---|
| EU AI Act (European Commission) | Four risk levels: unacceptable, high, transparency and minimal. The Act entered into force on 1 August 2024. The page gives 2 December 2027 for high-risk Annex III use cases and 2 August 2028 for high-risk systems embedded in products, after the AI Omnibus. It does not say which healthcare systems fall under which date | Classify each system by risk category and confirm on the official page whether a clinical product is in scope, and from when |
| FDA AI-enabled medical devices list | A resource listing AI-enabled devices authorised for marketing in the US. It states the list is not comprehensive and is updated periodically. It links FDA guiding principles on good machine learning practice, predetermined change control plans and transparency | Check whether a clinical AI product is a regulated device, and plan how model updates will be controlled |
| HIPAA Privacy Rule (HHS) | Sets federal baseline protections for protected health information and limits its use and disclosure without authorisation. Covers health plans, clearinghouses and providers that conduct certain transactions electronically | Confirm whether you are a covered entity or a business associate, and what data AI tools may touch |
| WHO, Ethics and governance of AI for health (2021) | Report with six consensus principles for AI that benefits the public | Reference for ethics review criteria; not a legal requirement |
Who is accountable, and how do we keep a record?
Accountability means a named person or committee owns each system, patients and staff can challenge an output, and the organisation can show what the system recommended, what the human did and which policy applied. Without that record, an incident review becomes guesswork.
This is where governance tooling helps. For example, ElixirData Context OS keeps governed context, versioned policy and decision traces in one decision layer above AI agents, and AgentGRC keeps autonomous agent actions inside policy, with the audit trail risk teams need, according to their own sites.
How should AI agents be governed in clinical and administrative work?
Agents differ from single models because they take actions across systems. Treat each action type as a decision with an owner, an allowed policy and a log entry. Administrative steps such as scheduling or coding suggestions can be automated earlier than anything that changes a care decision, which should keep a clinician in the loop. Our posts on agentic AI governance and compliance and agentic AI in healthcare go deeper. A platform such as ElixirClaw is described on its site as an agentic OS platform to build, orchestrate and govern AI agents and automation workflows while keeping humans in control.
What sequence should a healthcare organisation follow?
| Stage | Action | Evidence to keep |
|---|---|---|
| 1. Inventory | List every AI system and its intended use | Register with owner and risk category |
| 2. Classify | Check regulatory status (EU AI Act category, device status, HIPAA role) | Dated note citing the official page |
| 3. Validate | Test accuracy and subgroup performance on local data | Validation report and approved intended use |
| 4. Deploy with controls | Add explanation, override and consent steps | Runbook and sign-off |
| 5. Monitor | Track drift, incidents and complaints | Monitoring log and review minutes |
| 6. Review | Retrain, restrict or retire on set triggers | Change record |
When is a different approach better?
Do not add an AI system where a simpler rule or a human process meets the need safely, or where you cannot obtain representative data to validate it. Delay patient-facing automation until consent, disclosure and escalation routes exist. If a regulator has not confirmed whether your product is in scope, treat it as in scope for planning purposes and ask counsel.
To map one clinical or administrative decision your AI should make, and the context and policy it depends on, book a Context Workshop. See what happens in the workshop.
Frequently asked questions
What is ethical AI in healthcare?
Ethical AI in healthcare means designing, validating and running AI so that it protects patients, treats groups fairly, keeps health data private, can be explained to clinicians and stays under human accountability. In practice it is a set of controls that are tested and evidenced, not a statement of values.
Which regulations apply to AI in healthcare?
It depends on the market and the use. In the EU, the AI Act sets obligations by risk category. In the US, the FDA regulates AI-enabled medical devices and the HIPAA Privacy Rule covers protected health information held by covered entities. WHO guidance is not law but a widely used reference. Confirm the current position on each official page and with counsel.
Who is accountable when a clinical AI system gets it wrong?
The organisation that deploys the system must name an accountable owner, keep the record of what the system recommended and what the clinician did, and provide a route for patients or staff to challenge an output. This is a governance design choice, not something the model can supply.
How do we check an AI system for bias before go-live?
Compare the training and validation data with the population you will actually serve, test performance for each relevant subgroup, and set a threshold for retraining or withdrawal. Repeat the check when the patient population, device or clinical pathway changes.
Where should AI agents be allowed to act in a clinical setting?
Start with low-risk administrative steps, keep a human approving anything that changes care, and log every agent action with the policy that allowed it. Widen scope only when the audit trail shows the controls hold.
Related reading: Responsible AI in healthcare and explainability in healthcare AI.
Explore the XenonStack platform family: ElixirData · ElixirClaw · ElixirHub · NexaStack · MetaSecure · Neural AI · AgentGRC · AgentSRE · AgentAnalyst · AgentInstruct · AgentRAI · AgentScrum · AgentSearch · AgentForce · AI Aviator · SAIF Aviator · CohortIQ · XenonStack AI · XenonStack UAE
Follow XenonStack on LinkedIn: XenonStack on LinkedIn for new guides on agentic AI, data and platform engineering.